
Knowing When Dark Spots Need Assessment
When to See a Dermatologist for Pigmentation
Many dark marks are caused by melasma or inflammation and are not dangerous, but not every pigmented spot should be treated as routine hyperpigmentation. New, changing, unexplained or persistent pigmentation deserves the right diagnosis before stronger lightening products or procedures are used.
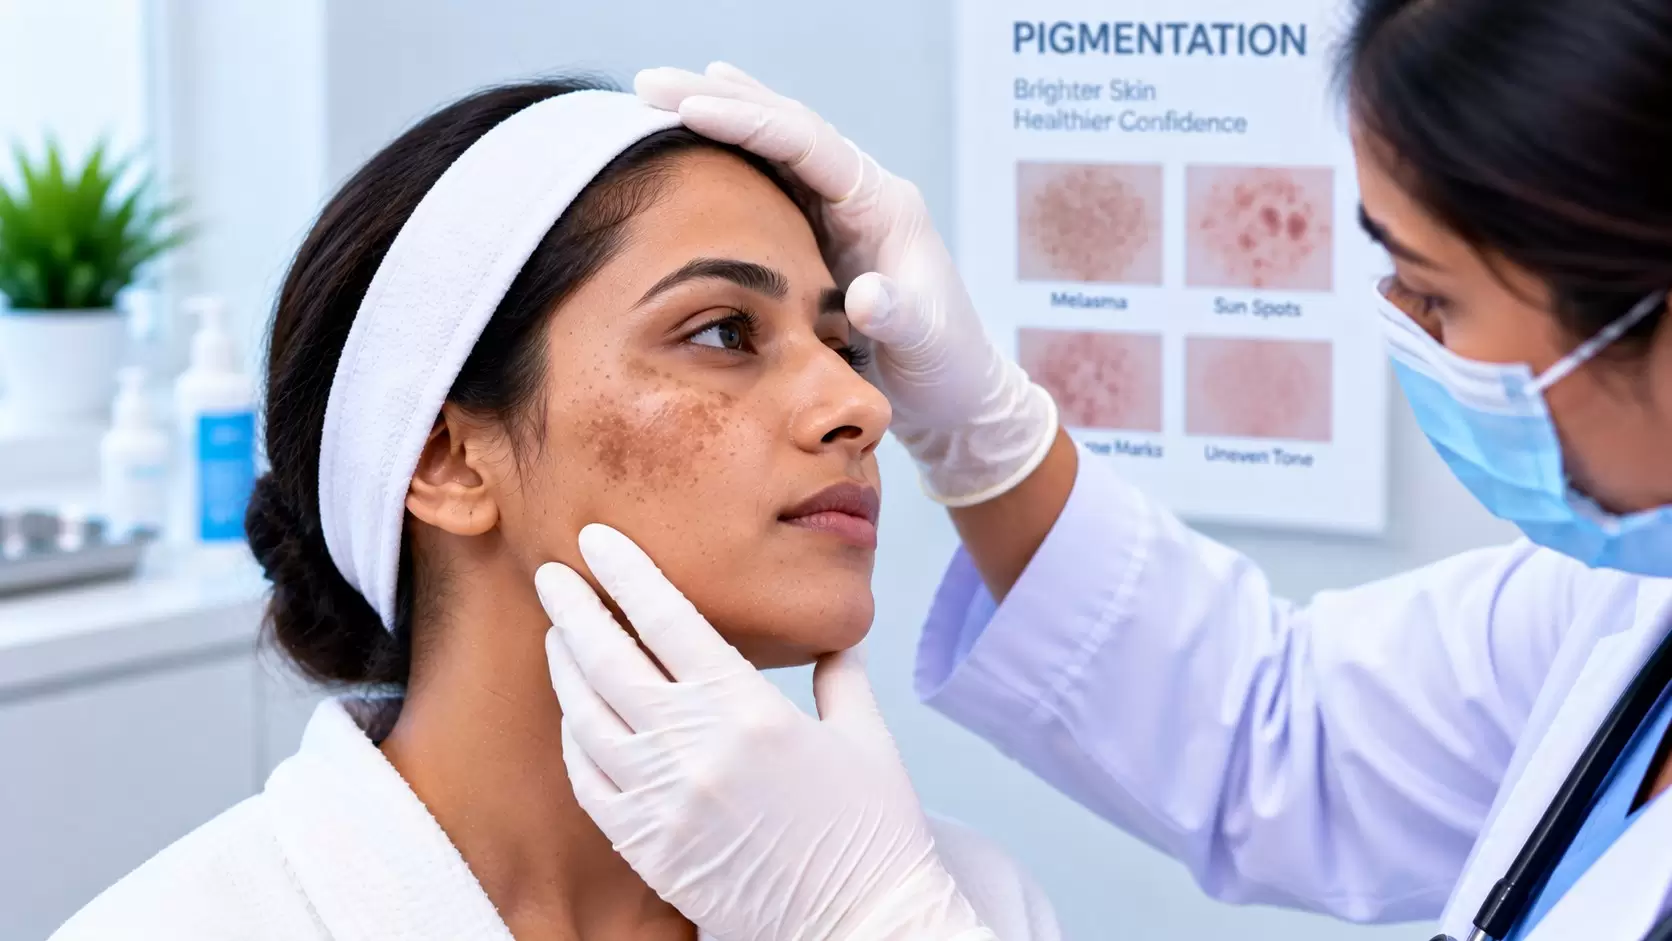
Why the diagnosis matters before treating pigmentation
“Pigmentation” describes a colour change, not a single diagnosis. Melasma, post-inflammatory hyperpigmentation, sun-related spots, medication-related pigmentation and individual pigmented lesions can look similar to an untrained eye.
A dermatologist can assess the pattern and decide whether the main issue is excess melanin, ongoing inflammation, a specific skin disorder or a lesion that needs separate evaluation.
Signs it is time to book a dermatology assessment
New or unexplained pigmentation
Darkening without an obvious trigger such as acne, rash or injury deserves assessment when it persists or progresses.
Persistent or recurrent patches
If pigmentation keeps returning despite consistent care, the trigger or diagnosis may need to be reviewed.
Changing individual spot
A mole or spot that grows, changes colour or shape, itches or bleeds should be examined promptly.
Treatment is irritating your skin
Burning, peeling and dermatitis can create additional PIH and may mean the routine needs adjustment.
1. Pigmentation that is new or unexplained
A new area of facial or body pigmentation may have a straightforward explanation, but persistent unexplained colour change should not automatically be labelled melasma.
The distribution, timing, medicines, preceding inflammation and associated symptoms all help narrow the cause. This is particularly important when the pigmentation does not follow a familiar pattern.
2. A dark spot that is changing
The American Academy of Dermatology advises assessment of a mole or spot that is growing, itching, bleeding or changing. Changes in symmetry, border, colour, diameter or evolution can also be warning signs that need examination.
This does not mean every changing spot is skin cancer, but a potentially suspicious lesion should be diagnosed rather than treated with bleaching creams, peels or lasers.
3. Pigmentation that keeps returning
Melasma is often recurrent, while PIH can keep appearing if acne, eczema or another inflammatory condition remains active.
When dark patches repeatedly return, the dermatologist can look for ongoing triggers and decide whether the maintenance plan needs to change.
Read Recurrent Pigmentation.
4. Pigmentation that is spreading
Gradually expanding pigmentation may still be benign, but spreading colour change deserves assessment when the cause is uncertain. Some inflammatory and acquired pigment disorders can extend beyond the typical distribution of melasma or acne marks.
A detailed history and examination can help distinguish these patterns and prevent months of inappropriate self-treatment.
5. Dark marks that do not improve
Post-inflammatory hyperpigmentation can take months to fade, and deeper pigment can persist much longer. Lack of rapid improvement therefore does not automatically mean something is wrong.
However, if the marks are not improving despite controlling the trigger and using consistent photoprotection, assessment can confirm the diagnosis and determine whether prescription treatment is appropriate.
6. Over-the-counter products are causing irritation
Products that repeatedly burn, sting or inflame the skin can cause additional pigmentation. Strong exfoliating acids, multiple active ingredients and unregulated lightening creams can all create problems.
A dermatologist can simplify the routine and select treatment based on the diagnosis and your skin’s tolerance rather than escalating irritation.
7. Acne keeps leaving new marks or scars
When active acne continues, every new inflamed lesion can leave another dark mark and sometimes a permanent scar. Treating the residual colour without controlling the acne creates an ongoing cycle.
Seek assessment when acne is persistent, painful, nodular, leaving repeated PIH or causing indented or raised scars.
For active acne, visit Acne Treatment in Chennai.
8. You are considering chemical peels or laser treatment
Procedures can help selected pigment problems but can also provoke post-inflammatory hyperpigmentation, particularly in pigment-prone skin. Melasma can relapse after some laser and light treatments.
Before a procedure, the diagnosis, skin tone, pigment depth, previous PIH and active inflammation should be considered. A procedure should not be chosen simply because a patch looks dark.
9. You are not sure whether it is melasma
Melasma commonly causes symmetrical brown or grey-brown facial patches, but several conditions can mimic it. A dermatologist can often diagnose melasma clinically and may use dermoscopy or a Wood’s lamp to examine the pigment more closely.
Occasionally a biopsy is needed when another condition needs to be excluded.
What happens during a pigmentation consultation?
The dermatologist will usually ask when the pigmentation started, how it has changed, whether there was preceding acne or rash, which products and medicines you use, and whether pregnancy, hormones or light exposure may be relevant.
The skin is then examined for distribution, colour and morphology. Dermoscopy can provide magnified detail, while a Wood’s lamp may sometimes help assess pigment depth or distinguish patterns.
Will you always need tests?
No. Many common pigment conditions, including melasma and straightforward PIH, can be diagnosed clinically from the history and examination.
Testing is selected when the presentation suggests another cause. Depending on the situation this might include a skin biopsy, patch testing or investigations for an associated medical condition.
What to bring to your appointment
Your skin-care products
Bring a list or photographs of cleansers, serums, creams, sunscreen and lightening products you use.
Your medicines
Some medicines can contribute to pigmentation or photosensitivity, so include prescription and non-prescription products.
Previous treatments
Note prior peels, lasers, facials and prescription creams, including whether they helped or irritated the skin.
Earlier photographs
Photos can help show how a patch or individual spot has changed over time.
When is pigmentation more likely to be a routine post-inflammatory mark?
A flat dark area that appears exactly where a pimple, eczema patch, insect bite or other inflammation recently healed is often PIH. These marks commonly fade gradually once the trigger is controlled.
Even so, seek assessment if the pattern is unusual, worsening, persistent or if you are uncertain whether the lesion is truly post-inflammatory.
When to seek prompt assessment
Arrange a dermatology assessment promptly for a pigmented spot or mole that is growing, changing shape or colour, bleeding, itching, becoming painful, or clearly looks different from your other spots.
Skin cancer can occur in all skin tones. In darker skin, suspicious lesions may also occur on palms, soles, nails and other areas that receive little sun, so unusual changing pigmentation at these sites should not be ignored.
Frequently asked questions
When should I see a dermatologist for pigmentation?
See a dermatologist when pigmentation is new, unexplained, changing, spreading, persistent, recurrent despite appropriate care, or when you are unsure whether a dark area is routine hyperpigmentation or a pigmented lesion.
What changes in a dark spot need prompt assessment?
A spot that is growing, changing in colour or shape, itching, bleeding, becoming painful or looks different from your other spots should be assessed promptly.
Should persistent melasma be assessed by a dermatologist?
Yes, especially when the diagnosis is uncertain, over-the-counter treatment has not helped, irritation is developing, or prescription treatment and procedures are being considered.
Can a dermatologist tell how deep pigmentation is?
Clinical examination, dermoscopy and sometimes a Wood’s lamp can help assess the pattern and depth of pigmentation. Occasionally biopsy is needed when another condition must be excluded.
When should I seek help for acne-related dark marks?
Assessment is useful when active acne keeps creating new marks, pigmentation is persistent, scarring is developing, or home treatment is irritating the skin.
Visit us in OMR
Concerned about persistent or changing pigmentation? Get the diagnosis right first.
Book a dermatologist consultation at Ram Skin Clinic in Thoraipakkam, Chennai.
#48, Second Floor, Flat E, Best Towers,Okkiampet, Thoraipakkam, OMR,
Chennai – 600097. Above Domino’s Pizza.
