
Folliculitis Types
Bacterial vs Fungal Folliculitis
Bacterial and yeast-related folliculitis can both cause acne-like bumps around hair follicles, but their typical distribution, symptoms, risk factors and treatment are different. Correct diagnosis matters because antibiotics do not treat yeast folliculitis, while antifungals do not treat bacterial infection.
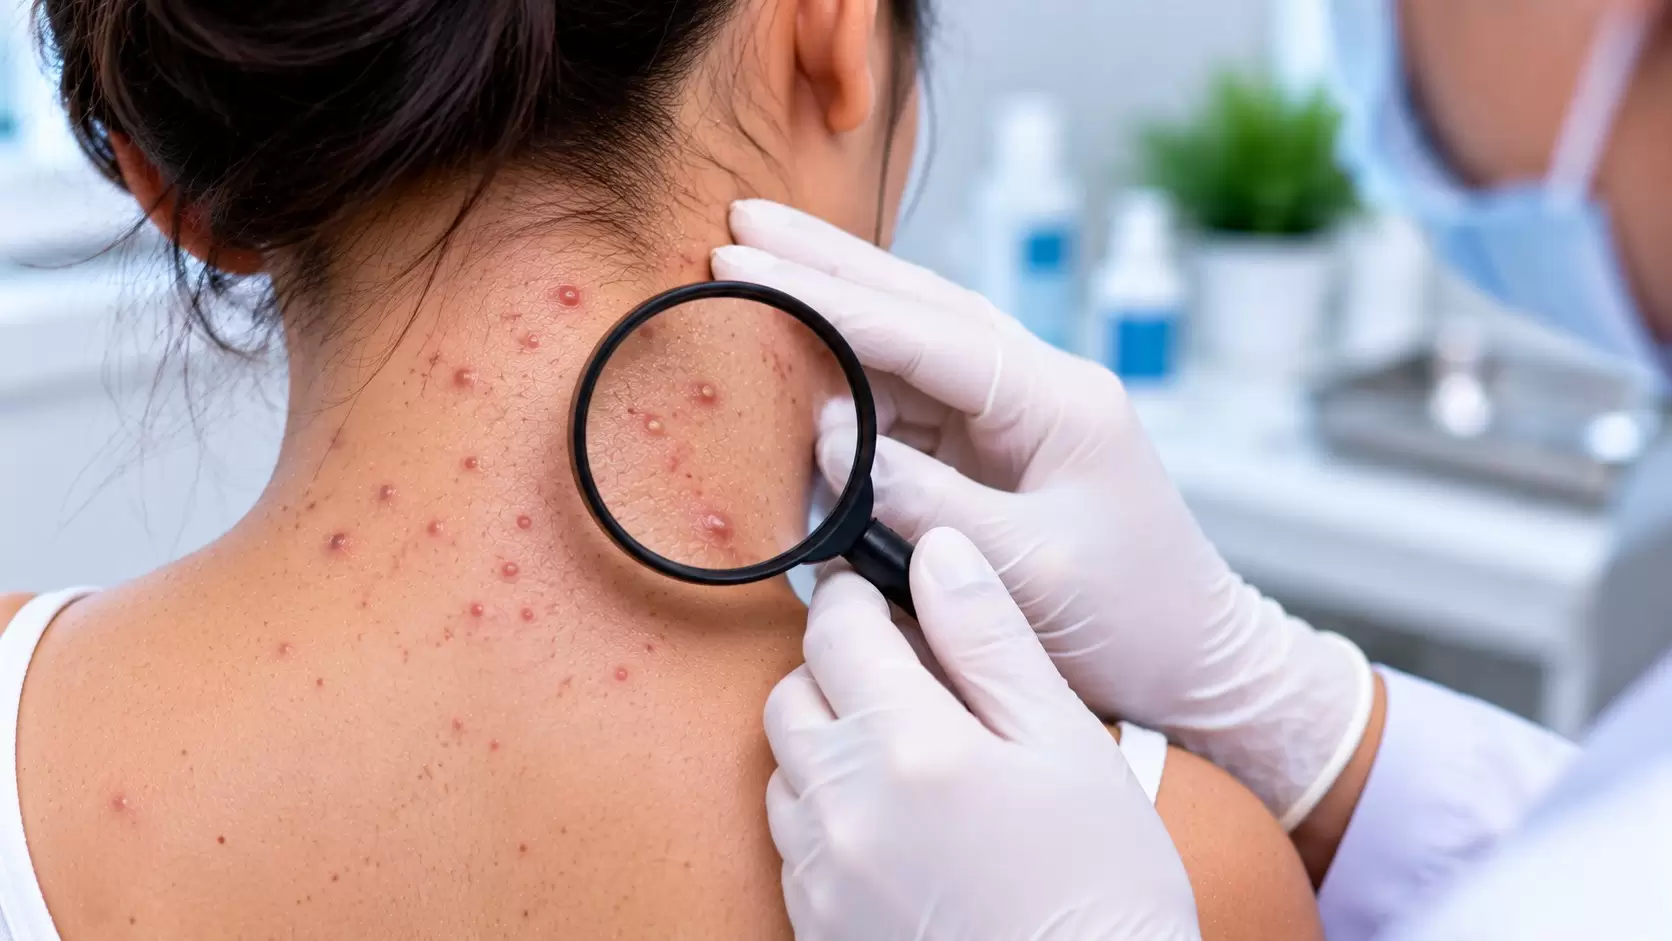
First, what does “fungal folliculitis” usually mean?
The term “fungal acne” is often used online for Malassezia folliculitis, but it is not acne. Malassezia is a yeast that normally lives on human skin. Under favourable conditions it can proliferate within hair follicles and produce an itchy follicular eruption.
DermNet describes Malassezia folliculitis as small, uniform, itchy papules and pustules, particularly on the upper back and chest, with possible involvement of the forehead, hairline, chin and neck. Comedones are not a feature.
Bacterial vs Malassezia folliculitis: key differences
| Feature | Bacterial folliculitis | Malassezia folliculitis |
|---|---|---|
| Common cause | Often Staphylococcus aureus | Overgrowth of Malassezia yeast |
| Typical lesions | Follicular pustules or inflamed bumps; lesions may vary in size | Small, very similar-looking follicular papules and pustules |
| Itch | Can itch, but may be more tender or sore | Itch is a prominent feature |
| Common sites | Any hair-bearing skin, often beard area, scalp, buttocks or limbs | Upper back, chest, forehead/hairline, chin and neck |
| Comedones | Not typical of folliculitis | Absent |
| Treatment direction | Antibacterial measures when infection is confirmed/suspected | Topical or oral antifungal therapy depending on severity |
These are patterns rather than a home diagnostic test. Mixed or atypical presentations occur, and acne can coexist with folliculitis.
Signs that suggest bacterial folliculitis
Tender pustules
Superficial bacterial folliculitis often creates pus-filled spots centred on follicles. The surrounding skin can be inflamed and tender.
Deeper painful lesions
When infection extends deeper into a follicle it can produce a painful boil or furuncle.
After shaving or friction
Damaged follicles from shaving, waxing, rubbing or occlusion can provide an entry point for bacteria.
Recurrent episodes
Repeated staphylococcal folliculitis may justify bacterial culture and evaluation of ongoing risk factors.
For the broader overview, read Folliculitis Causes & Symptoms.
Signs that suggest Malassezia folliculitis
Malassezia folliculitis tends to be monomorphic: many lesions look very similar in size and shape. DermNet notes that itching is common and that lesions frequently occur on the upper trunk, forehead and hairline.
Risk factors described by DermNet include hot humid climates, high sebum production, hyperhidrosis, occlusion from emollients or sunscreens, recent antibiotic use, corticosteroid use and immune suppression.
Why antibiotics can sometimes make the confusion worse
Antibiotics may be appropriate for bacterial folliculitis, but they do not treat Malassezia yeast. DermNet identifies antibiotic use as a risk factor for Malassezia folliculitis, likely because altering the skin microbial environment can favour yeast proliferation.
This is one reason recurrent “acne” or folliculitis that does not respond as expected should be reassessed rather than repeatedly treated empirically.
How dermatologists tell the difference
The distribution, uniformity of lesions, degree of itching, presence or absence of comedones, medication history, shaving habits and response to previous treatments all provide clues.
When the diagnosis is uncertain, DermNet describes laboratory confirmation for Malassezia using skin scraping, tape stripping, swab or biopsy. Mayo Clinic notes that folliculitis evaluation may include scraping for yeast, bacterial culture and, rarely, skin biopsy.
Testing is particularly useful when folliculitis is recurrent, widespread or not responding to an apparently appropriate treatment.
What about other fungal folliculitis?
Malassezia is not the only fungal or yeast-related cause of follicular inflammation. DermNet notes that dermatophyte infection can occasionally produce folliculitis, particularly in areas such as the beard region or scalp.
Because different organisms require different therapy, the generic label “fungal folliculitis” can be misleading without identifying the actual cause.
Treatment depends on the cause
Mild bacterial folliculitis can sometimes settle with appropriate hygiene and avoidance of triggers, while persistent or extensive bacterial disease may need clinician-directed topical or oral antibiotics. Recurrent cases may require culture to identify the organism and antibiotic susceptibility.
Malassezia folliculitis is treated with antifungal therapy. DermNet lists topical options such as selenium sulfide, econazole and ketoconazole and notes that systemic treatment may be used in some cases. Recurrence can occur, so maintenance topical therapy may sometimes be helpful.
Could it actually be acne?
Acne can involve papules and pustules too, but comedones—blackheads and whiteheads—support acne rather than Malassezia folliculitis. Acne lesions are also often more varied, with a mixture of comedones, inflammatory papules, pustules and sometimes nodules.
Our next comparison article, Folliculitis vs Acne, explains these differences in detail.
When should you see a dermatologist?
Arrange assessment if the eruption is widespread, recurrent, very itchy or painful, leaves marks, does not improve with appropriate care, or keeps returning after antibiotics or antifungal treatment. These patterns make confirming the diagnosis especially important.
For evaluation and treatment, visit Folliculitis Treatment in Chennai.
Frequently asked questions
How can I tell bacterial folliculitis from fungal folliculitis?
Bacterial folliculitis often causes tender pustules, while Malassezia folliculitis commonly causes very itchy, uniform small follicular bumps on the upper trunk or hairline. However, appearance alone may not reliably identify the cause.
Is fungal acne actually acne?
No. The term “fungal acne” usually refers to Malassezia folliculitis, an inflammatory disorder of hair follicles caused by yeast rather than acne vulgaris.
Does Malassezia folliculitis have blackheads?
No. Comedones such as blackheads and whiteheads are not a typical feature of Malassezia folliculitis.
Can antibiotics make fungal folliculitis worse?
Antibiotics do not treat Malassezia, and antibiotic use is recognised as a risk factor for Malassezia folliculitis. Persistent symptoms after antibiotics should be reassessed.
Can bacterial and fungal folliculitis be tested?
Yes. Depending on the presentation, a dermatologist may use bacterial culture, skin scraping or other laboratory methods to help identify the cause.
Why does my folliculitis keep coming back?
Recurrence can result from persistent infection, yeast overgrowth, sweating, occlusion, shaving, friction, medication effects or an incorrect initial diagnosis.
For authoritative information, see DermNet on bacterial folliculitis, DermNet on Malassezia folliculitis and Mayo Clinic.
Visit us in OMR
Not sure what is causing your folliculitis?
Book a dermatologist consultation at Ram Skin Clinic in Thoraipakkam, Chennai.
#48, Second Floor, Flat E, Best Towers,Okkiampet, Thoraipakkam, OMR,
Chennai – 600097. Above Domino’s Pizza.
